Why Your Heart Rate Runs Higher at the Same Effort in Perimenopause
Quick Answer: Several perimenopausal changes push heart rate up at a given workload: reduced plasma volume means each beat moves less blood, poorer sleep raises resting and submaximal heart rate, hot flushes and impaired thermoregulation add cardiovascular load, and shifting oestrogen affects vascular function and autonomic balance. It usually indicates changed physiology rather than lost fitness. The practical response is to train by effort and pace rather than by heart rate zones, and to note that a persistently elevated resting heart rate is worth a medical conversation rather than an assumption.
Same route, same pace, same shoes, ten beats higher than last year.
The watch is not broken and your fitness has usually not collapsed. Something underneath has moved.


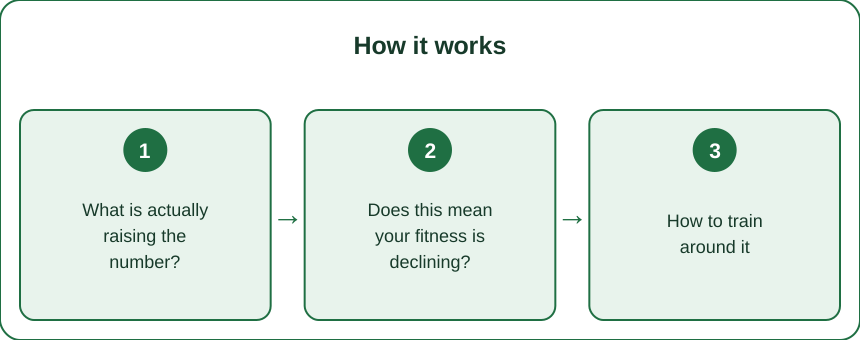
What is actually raising the number?
Plasma volume tends to decline, and lower blood volume means a smaller stroke volume - so heart rate has to rise to deliver the same cardiac output. This is one of the more direct mechanisms.
Sleep disruption is extremely common in perimenopause and raises both resting and submaximal heart rate independently. A few consecutive poor nights alone can account for several beats.
Thermoregulation changes. Hot flushes and altered heat dissipation mean more blood diverted to the skin during exercise, which raises heart rate for the same muscular work - and does so most in warm weather, which is why the effect looks worse in August.
Oestrogen affects vascular function and autonomic balance, including a general shift toward greater sympathetic dominance, and both influence heart rate at rest and during exercise.
Iron status is worth checking, since heavier or irregular bleeding is common in perimenopause and low ferritin raises heart rate at any given workload very reliably.
And hydration, alcohol and stress all sit on top of this, each capable of moving submaximal heart rate several beats on their own.
Does this mean your fitness is declining?
Not necessarily, and usually not by as much as the number suggests. If your pace, power and perceived effort are stable, elevated heart rate at the same output is describing the cost of delivery rather than the output itself.
Pace and power are outcome measures; heart rate is an input measure. When they diverge, the outcome measure is the more reliable indicator of fitness.
Perceived effort is genuinely useful here and is often more stable across this transition than heart rate is. If a run that used to feel easy still feels easy, the fitness is probably intact.
Heart rate zones calculated from an old maximum or an old lactate threshold will be wrong, which is a common source of unnecessary alarm. Zones need re-establishing periodically at any age and particularly during this transition.
Some decline in maximal capacity does occur with age, and separating that from the perimenopausal changes described above is difficult without testing. Both are usually contributing something.
And training adaptations still happen normally. Strength, endurance and body composition all respond to training in perimenopause; the monitoring metrics are what need reinterpreting.

How to train around it
Train by pace, power and perceived effort rather than by heart rate. This is the single most useful adjustment, and it removes most of the confusion immediately.
Re-test your zones if you use them, rather than carrying forward numbers established years ago. A field test twice a year is enough.
Prioritise strength training. Resistance training addresses bone density, muscle mass and metabolic health, all of which are directly affected in this period, and it is less confounded by these heart rate changes than steady cardio is.
Adjust for heat deliberately. Train earlier in the day in late summer, and expect higher heart rates and slower paces in warm conditions - this is exaggerated in perimenopause rather than new.
Attend to sleep as a training variable, because it affects heart rate, recovery and training quality more in this period than it did previously.
And ask for iron studies including ferritin if bleeding has been heavy, since low iron is common, very treatable, and produces exactly this symptom picture. This is general information, not medical advice.
Myth vs Fact: Perimenopause and Heart Rate
Myth: a higher heart rate at the same pace means you have lost fitness. Fact: it can indicate reduced plasma volume, poor sleep or heat load. If pace and effort are stable, fitness likely is too.
Myth: you should train harder to fix it. Fact: training harder while under-recovered raises heart rate further. The answer is more often better sleep and adequate iron than more intensity.
Myth: heart rate zones are fixed once calculated. Fact: they shift with fitness, age, heat, altitude and hydration, and they need re-establishing periodically regardless of life stage.
Myth: it is all hormonal and nothing can be done. Fact: sleep, iron status, hydration, heat acclimation and training structure are all modifiable and account for a substantial share of the change.
Myth: a raised resting heart rate is just part of it. Fact: a persistently elevated resting heart rate, palpitations, or breathlessness disproportionate to effort should be discussed with a clinician rather than attributed to perimenopause by default. This is general information, not medical advice.
FAQ: Heart Rate in Perimenopause, Answered
How many beats is normal?
There is no established figure, and individual variation is large. What matters more is the pattern - a stable elevation alongside stable pace and effort is different from a rising trend alongside falling performance.
Should I stop using my heart rate monitor?
No - it is still useful for tracking trends over weeks and for spotting the days when something is genuinely off. Just stop using it as the primary way to prescribe intensity.
Does HRT change this?
Some people report changes in heart rate and exercise tolerance on HRT, and effects vary considerably between individuals. That is a conversation for your clinician rather than a general rule.
What about hot flushes during exercise?
They add cardiovascular load and are more likely in warm conditions. Training in cooler parts of the day and dressing in layers you can shed both help materially.
When should I get this checked?
Resting heart rate persistently elevated well above your normal, palpitations, chest discomfort, breathlessness out of proportion to effort, or fainting all warrant prompt medical attention rather than a training adjustment. This is general information, not medical advice.
TL;DR:
- Reduced plasma volume, disrupted sleep, altered thermoregulation and vascular changes all raise heart rate at a given workload.
- Stable pace, power and perceived effort mean your fitness is probably intact even if the number is higher.
- Train by effort and pace rather than heart rate zones, and re-test zones twice a year rather than carrying old ones forward.
- Ask about iron studies including ferritin if bleeding has been heavy - low iron produces exactly this picture and is very treatable.
- Prioritise strength training, which addresses bone and muscle directly and is less confounded by these changes.
Persistently elevated resting heart rate, palpitations or breathlessness out of proportion to effort deserve medical attention rather than assumption. This is general information, not medical advice.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
