Why Perimenopause Wakes You at 3 A.M. Specifically - and What Actually Helps
Quick Answer: The 3 a.m. cluster comes from three things converging: cortisol begins its natural morning rise in the small hours, sleep becomes lighter in the second half of the night, and the hormonal fluctuations of perimenopause make it easier for a hot flash or a stress response to break through at exactly that lighter stage. You are not waking randomly - you are waking during the shallowest sleep of the night at the moment cortisol is climbing. What helps most: keeping the room genuinely cold, protecting the first half of the night, and refusing to problem-solve while awake.
The goal is not to eliminate the waking. It is to shorten it.
This is general information, not medical advice.


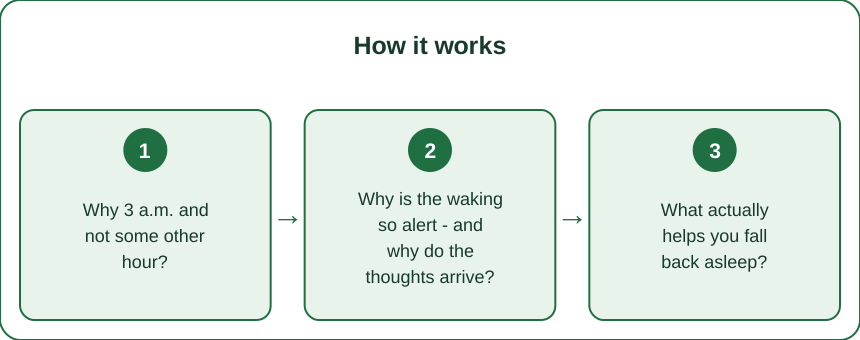
Why 3 a.m. and not some other hour?
Because sleep architecture and hormone timing collide there.
Deep slow-wave sleep is front-loaded. Most of it happens in the first few hours after you fall asleep. By the second half of the night, sleep is dominated by lighter stages and REM - stages from which you wake easily.
Cortisol starts rising in the small hours. The cortisol awakening response begins well before you get up, typically climbing from around 2-3 a.m. toward a peak shortly after waking. A rising cortisol curve meeting light sleep is a wake-up waiting for a trigger.
And perimenopause supplies the trigger. Fluctuating estrogen affects thermoregulation, and a hot flash or night sweat during light sleep will wake you where the same event during deep sleep might not. Progesterone, which has a calming, sleep-supporting effect, also declines through perimenopause - and that decline removes some of the buffer that used to keep you under.
The result is a cluster, not a random distribution. Which is oddly reassuring: a predictable mechanism is a mechanism you can work with, and the interventions below all target one of the three components.
Why is the waking so alert - and why do the thoughts arrive?
Because a cortisol-driven wake is a different kind of wake.
Cortisol is an activating hormone. Waking at the top of a cortisol rise means waking alert rather than groggy, which is why 3 a.m. wakings feel so much more wide-awake than a 6 a.m. alarm does.
And an activated nervous system recruits worry. The brain in a mildly activated state at night preferentially surfaces threat-related content - which is why the thoughts that arrive at 3 a.m. are never pleasant ones, and why they seem so much more serious than they will at 9 a.m.
The catastrophizing is a state, not an insight. Nothing you conclude at 3 a.m. deserves to be acted on. The single most useful reframe available is that the content of 3 a.m. thinking is a symptom of the hour, not information about your life.
Then the loop closes. Frustration about being awake raises arousal, which makes returning to sleep harder, which increases frustration. The frustration is doing more damage than the original waking. Which is why the most effective interventions target the response rather than the trigger.
What actually helps you fall back asleep?
In order of how much they matter.
Keep the room genuinely cold - around 60-67°F. This is the highest-value change. Core temperature must drop for sleep to consolidate, and a cool room gives you margin against a hot flash that would otherwise wake you fully. Cool room, layered bedding you can throw off in seconds.
Do not look at the clock. Knowing it is 3:14 starts the arithmetic about how much sleep is left, which is pure arousal. Turn the clock around.
Get up after about 20 minutes. If you are still awake and frustrated, leave the bed. Lying awake trains your brain to associate the bed with wakefulness. Sit somewhere dim, read something undemanding on paper, and return when sleepy.
Keep the lights very low. Bright light suppresses melatonin and signals morning. Dim, warm light only.
Have a mental parking place. A notepad by the bed for the thought that will not leave. Writing it down genuinely releases the loop - the brain rehearses what it fears forgetting.
Slow the breathing out. Extended exhales activate the parasympathetic system. Four in, six or eight out, for a few minutes. The mechanism is real and it costs nothing.
And treat the sweat directly if that is your trigger: moisture-wicking sleepwear, a cotton or bamboo layer over the mattress, and something absorbent within reach so a night sweat does not require a full reset.

What Nobody Tells You About Perimenopause Sleep
Five things that change the approach.
The first half of the night is the part worth protecting. That is where the deep, restorative sleep lives. Alcohol is the biggest threat to it - it helps you fall asleep and then fragments the second half badly, in exactly the window that is already fragile. One evening drink can turn a manageable 3 a.m. waking into a 2 a.m. one that lasts two hours.
Waking at night is not the same as insomnia. Brief night wakings are normal across the lifespan, and most people fall back asleep without remembering. What changes in perimenopause is how easily you come fully awake and how hard it is to return. That is a smaller problem than it feels like at the time.
Daytime consequences are mostly about the second half of the night. Which is why total hours can look adequate on a tracker while you feel terrible - fragmented light sleep does not do the same job as consolidated sleep, and a device that reports seven hours is not lying, just not measuring what matters.
Exercise helps but the timing matters more than usual. Morning or early afternoon movement supports sleep. Vigorous evening exercise raises core temperature at the wrong end of the day for someone already fighting thermoregulation.
And it does resolve for most people. Sleep disruption is commonly worst through the perimenopausal transition and improves afterward. This is a phase with an ending, which is not a small thing to know at 3 a.m.
Does the season change anything?
More than people expect, and late summer into fall is a specific pressure point.
Warm nights remove your thermal margin. A bedroom that sits at 74°F overnight in August leaves nothing between a hot flash and a full wake-up. Cooling the room is more valuable now than at any other time of year - a fan, a cooling mattress layer, or simply less bedding.
Then the light shifts fast. From late August onward, sunrise moves later at a steady clip, and circadian timing drifts with it. A body that had settled into a summer rhythm gets a moving target.
The fix is morning light. Getting outside within an hour of waking anchors the rhythm and, over days, improves both sleep onset and the ability to fall back asleep after a waking. This is one of the few interventions with a strong effect and no downside, and it becomes harder to remember exactly when it starts mattering more.
Schedules also tighten in September. Later evenings, more obligations, and a compressed wind-down all reduce the buffer before bed. Protecting a genuine 30-minute wind-down is worth more in a busy season than in a quiet one.
And keep the wake time steady, even after a bad night. A consistent wake time is the anchor that holds the whole rhythm together. Sleeping in to compensate feels like repair and functions as further disruption.
FAQ: 3 A.M. Waking Questions, Answered
Should I just get up and start my day?
Only if it is close to your normal wake time. Getting up at 3 a.m. regularly moves your whole rhythm earlier and creates a new problem. Get out of bed, yes; start the day, no.
Does magnesium help?
Some people find it useful, and the evidence is mixed rather than strong. It is low-risk for most people, and it is not a substitute for room temperature, light timing, and alcohol - which have much larger effects. Worth discussing with your doctor, particularly alongside other medications.
When should I talk to a doctor about this?
If it is happening most nights, if it is affecting daytime function, or if you snore or wake gasping - sleep apnea becomes more common after menopause and is frequently missed. Hormone therapy and other treatments are worth discussing. This is general information, not medical advice.
TL;DR:
- 3 a.m. is when light sleep meets a rising cortisol curve - the timing is a mechanism, not bad luck.
- The alert, anxious quality is cortisol. Nothing you conclude at 3 a.m. deserves to be acted on.
- A genuinely cold room, 60-67°F, is the single highest-value change.
- Get out of bed after 20 minutes, keep lights dim, and write the sticky thought down.
- Protect the first half of the night - evening alcohol damages exactly the sleep you can least afford to lose.
- Morning light and a fixed wake time hold the rhythm together as the days shorten.
Start with the thermostat and the clock facing the wall tonight. Those two take one minute and address the two biggest contributors. This is general information, not medical advice.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
